

Can Medication Improve Crown Thinning Enough to Avoid a Hair Transplant?
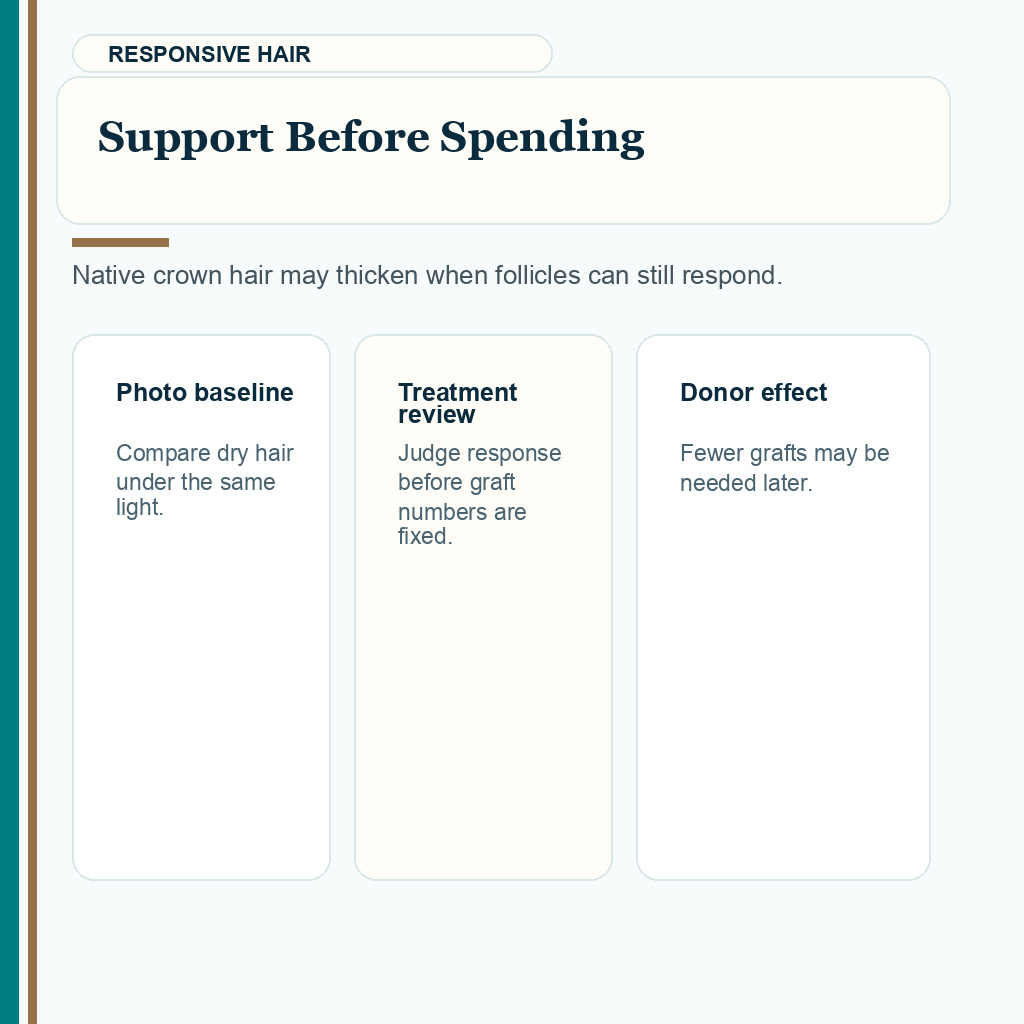
Medication can sometimes improve crown thinning enough to delay, reduce, or occasionally avoid a hair transplant, but only when there is still native hair that can respond. If the crown is already slick, shiny, and empty, medicine cannot be promised to rebuild full coverage. The decision is not simply medicine or surgery. It is whether the crown still has miniaturized hair worth supporting before donor grafts are spent.
For that reason, I do not answer a crown photo with only a graft number before checking native hair and medication response. I first decide whether I am seeing a normal whorl, early androgenetic crown thinning, a crown that still has useful native hair, or an area that has already crossed into a surgical coverage problem. The answer changes the plan.
The crown decision starts with native hair
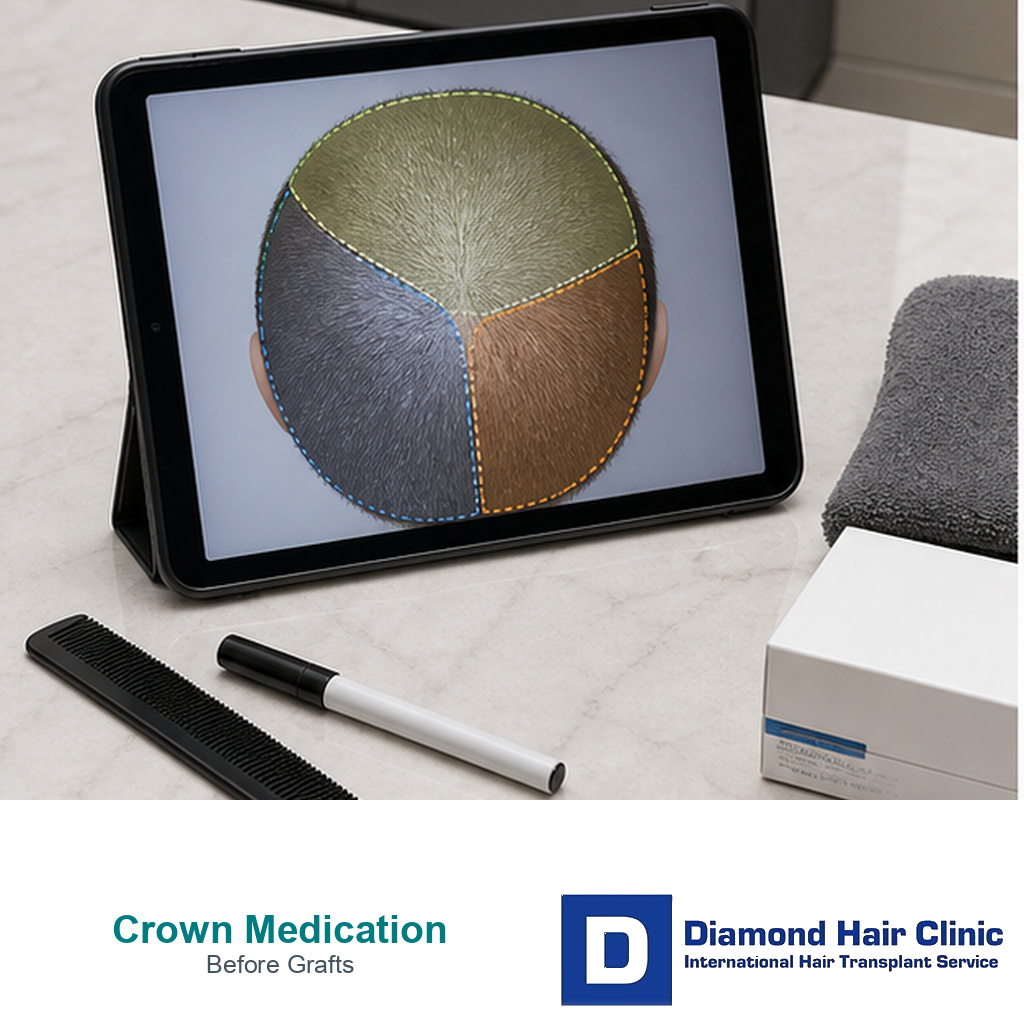
The crown is different from the hairline. Hair turns around a whorl, opens in several directions, and catches overhead light. A patient can look much thinner from one bathroom photo than he looks in normal life. Before I discuss crown hair transplant planning, I need dry photos, consistent lighting, donor review, age, family history, medication history, and the amount of miniaturized hair still present.
Send dry hair and parted crown photos before deciding medication failed. Overhead light, wet hair, and a tight swirl can make a responding crown look worse than it is. Keep the haircut similar during the review period, because a shorter crown can make a stable response look like sudden failure.
Medication works through native follicles that are still alive enough to respond. It can support miniaturized hair, improve caliber in some patients, reduce shedding, and slow progression. It does not create unlimited donor hair. It does not change a fully bald crown into dense teenage coverage. That distinction protects the patient from two extremes, rushing into grafts too early and waiting forever for a medical result that is unlikely.
The medication boundary still matters after crown surgery. Medication may help protect responsive native hair around the transplanted area, but it cannot create dense coverage beyond the donor budget that was already spent. If the crown looks thinner only when wet or under overhead light, I separate that optical test from true medical progression.
I also separate the crown from the front. If the hairline and mid scalp are unstable, the crown may not deserve the first graft budget. A crown can consume many grafts and still show some scalp under strong light. When donor supply is limited, a restrained crown plan or a period of medical observation can be wiser than treating the crown as the only emotional problem.
Realistic medication changes
Finasteride, dutasteride, topical minoxidil, and oral minoxidil are not the same decision, and they are not suitable for every patient. Finasteride and topical minoxidil are common male pattern hair loss options. Dutasteride or oral minoxidil need a more deliberate prescribing review before they are treated as routine choices. The plan still needs side effect discussion and realistic follow up. But in a crown that still has miniaturized hair, medication may improve the surgical map. It can make the crown look stronger, show whether the area is still changing, or reduce the number of grafts needed later.
That is the useful version of medication can delay hair transplant surgery. Delay is not a way to avoid responsibility. It is useful only when the delay gives the patient better information or preserves donor grafts. A medical trial that shows improvement may make surgery smaller. A trial that shows no response may make the surgical decision clearer.
Minoxidil deserves its own distinction. If it has made the crown or mid scalp look stronger, that supported hair is real, but it may depend on continued treatment. For that reason, minoxidil timing around hair transplant surgery should not be guessed from another patient’s routine. A long stop can change the visible map. A topical pause for scalp cleanliness is a different issue from removing medical support for months.

Useful waiting before crown grafts
Waiting is useful when the crown still has visible miniaturized hair, the patient is young, the family pattern is still declaring itself, the donor reserve is limited, or the front has not been planned. In those cases, the crown can become a graft sink. A rushed crown operation may spend donor supply before the true future shape is visible.
Before crown graft numbers are locked, the medication review before a hair transplant has to show what changed, what helped, what caused side effects, and what the patient can realistically continue. The useful baseline is not the best photo after styling or the worst photo after shedding. It is a fair comparison that shows whether the crown is becoming easier or harder to plan.
When the mid scalp and crown are the main concern, a new response can change the order of surgery. Improvement in miniaturized native hair may reduce crown graft demand, while a bare crown still needs realistic coverage planning. I do not treat PRP or tablets as a promise of teenage density. I use them only if they make the crown map more reliable.
A useful waiting period has a job. It should test whether native hair can be supported, whether shedding settles, whether side effects are tolerable, and whether the crown is expanding. Waiting without photos, follow up, or a clear review point becomes avoidance. Surgery without that review can become waste.
The crown is where choosing surgery instead of medicine can spend donor grafts fastest. If medication support is not realistic, I reduce the crown ambition before I reduce the future safety margin.
Low response crowns need different planning
Medication is less likely to avoid a crown transplant when the crown is mostly bare, shiny, and low response, or when the patient has already used a supervised treatment plan long enough to judge the pattern and the crown remains cosmetically unacceptable. At that point, I do not keep promising medical rescue. I discuss what surgery can and cannot do.
The graft number still has to be calculated carefully. How graft numbers are calculated depends on surface area, hair thickness, skin contrast, curl, density target, donor strength, and what must be saved for future loss. A smaller crown may need a moderate plan. A wide crown can ask for many grafts and still not look completely full in bright overhead light.
If the donor area is weak, the discussion becomes more conservative. A weak donor and high graft quote conflict should make the patient slow down, not chase the largest crown number. A surgeon has to protect the hairline, mid scalp, later progression, and possible repair work, not only improve the circle that bothers the patient today.
SMP changes contrast, not hair count
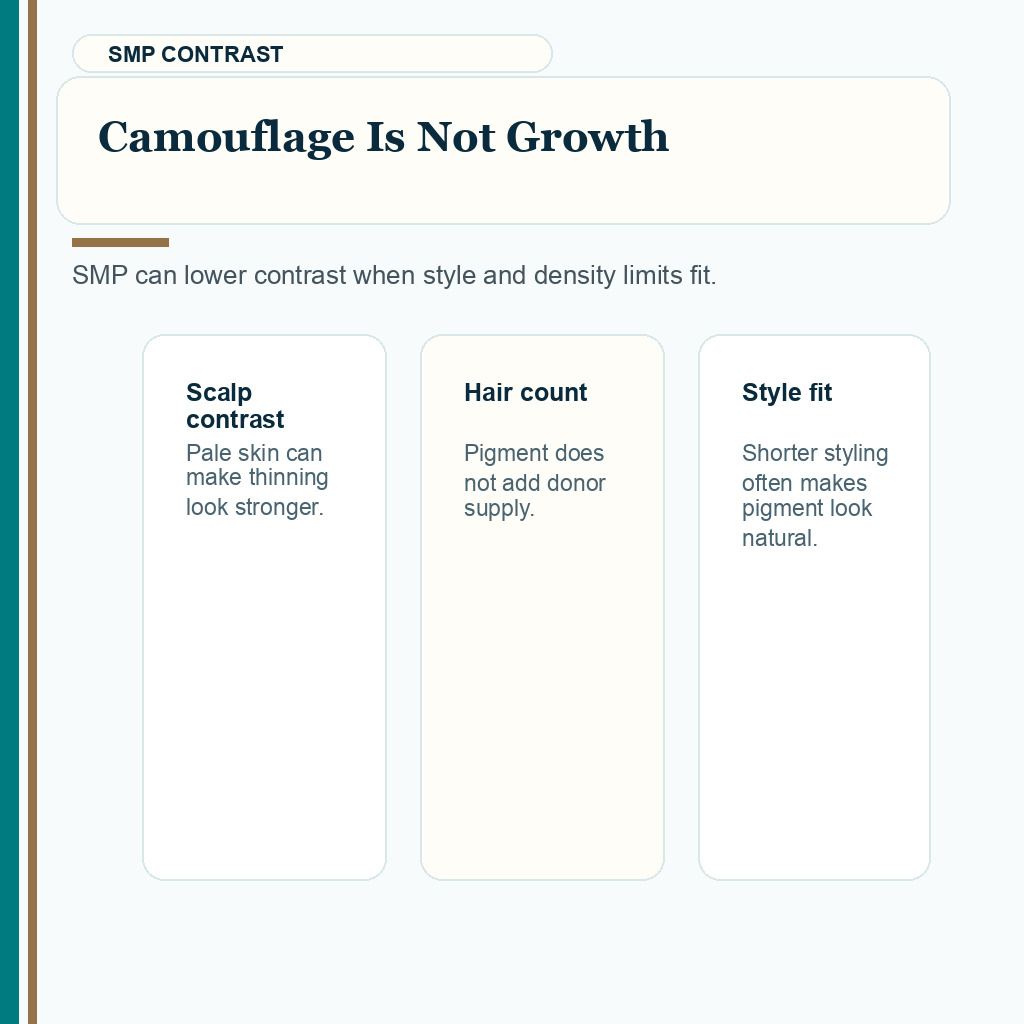
Scalp micropigmentation can be useful in selected crown cases, especially when the patient has some hair, partial transplant coverage, short styling, or strong scalp contrast. But SMP is camouflage. It can reduce the pale scalp effect. It does not grow hair, increase donor supply, stabilize androgenetic loss, or correct wrong graft direction.
I place SMP for thin hair after transplant in a different category from medication and surgery. Medication supports responsive native follicles. Surgery moves donor grafts. SMP changes the optical background. Mixing these three categories can lead to poor decisions because the patient starts expecting one tool to do another tool’s job.
SMP may reduce the number of grafts needed to meet an optical contrast goal in selected cases, but it should not be used to excuse a bad donor plan. If the patient wants long hair, high density, and no visible scalp under all light, SMP will not create that. If the patient accepts short styling and optical improvement, it may be part of a conservative crown strategy.
Use the route map before spending grafts
For a crown medication question, I put the case into one of four routes. The route matters more than the label of the treatment.
A no medication crown plan needs extra donor discipline because the crown can keep expanding while the frontal frame still needs reserve. I do not treat a laser cap or a later second surgery as permission to spend grafts in the crown before the pattern is readable.
Crown response route map
Choose the crown route before the graft number
- Native hair still presentTest response first
- Mostly slick crownRegrowth limit
- Donor reserve is tightSpend grafts slowly
- Scalp contrast is the main issueSeparate SMP from growth
Test response first
Miniaturized crown hair may thicken or stabilize when it can still respond. This is the group where medication may delay, shrink, or occasionally avoid crown grafting.
Next move Use comparable photos and medical review before locking the graft count.
Regrowth limit
When the crown is shiny, bare, and low response, medicine may protect nearby hair but should not be sold as full crown restoration.
Next move Discuss realistic crown surgery, SMP camouflage, or accepting a thinner crown.
Spend grafts slowly
A crown can consume many grafts while the front, mid scalp, or future repair still needs supply. Medication response can help decide whether the crown deserves grafts now.
Next move Prioritize the whole scalp plan, not only the round area in the photo.
Separate SMP from growth
If the main problem is pale scalp showing through some existing hair, SMP may reduce contrast, but it does not grow hair or increase donor supply.
Next move Use SMP only when the style, maintenance, and density expectation fit.
If finasteride is not tolerated, the plan still has to be made with restraint. Hair transplant without finasteride can be planned in selected patients, but the donor use and future loss expectation change. I do not punish a patient for side effects. I also do not pretend the long-term crown risk is the same.
The same applies to patients already using oral minoxidil in transplant planning. It is a systemic medication. I want the prescribing doctor and the surgical team involved, especially when there are blood pressure, swelling, dizziness, heart, or medication change concerns.
Reassessment after a treatment window
Reassessment should not be done from one harsh photo. I want comparable crown photos with dry hair, similar length, similar lighting, and the same angle. I also want to know whether the patient changed treatment, stopped treatment, developed side effects, or started another medication. If the crown looks stronger under fair comparison, grafts may be delayed or reduced. If the crown is still expanding, surgery may need to wait or become more restrained. Needing less concealer or fewer fibers under the same conditions can be more useful than one perfect crown photo.
A few new crown hairs can be encouraging without being enough to cancel surgery. The more useful sign is a crown that becomes more predictable under the same light and hair length, not only a small group of new hairs that disappears under overhead light.
When surgery was booked before the treatment response became clear, I still recheck the crown before grafts are removed. A booking date should not freeze an old plan if the current donor exam and comparable clinical review suggest that the crown now needs fewer grafts or more time before surgery.
The best sign is not a miracle photo. The best sign is a crown that becomes more predictable. Predictability lets me plan donor grafts with less waste. It also tells me whether the surrounding native hair may continue to need support after surgery. Finasteride before and after hair transplant is part of that wider native hair discussion for suitable patients, not a promise that everyone must use it.
If the treatment helps but not enough, the surgical plan may become smaller. That can still be a win. A smaller crown operation can preserve grafts for the front, mid scalp, or future repair. It can also create a softer, more natural improvement than trying to force dense coverage across a wide rotating surface.
Partial response to PRP or medication should not be used as proof that the crown is solved. It can reduce pressure on grafts, show the donor budget more clearly, or reveal that the crown is still changing. That information is useful, but it does not make a weak donor decision safer by itself.
A smaller crown operation can be a real win
Some patients hear “avoid surgery” and think success only means never needing a transplant. I see it differently. Sometimes success is delaying until the pattern is clearer. Sometimes it is reducing a large crown request into a restrained use of grafts. Sometimes surgery is right, but only after medication has shown what native hair can still do.
In the crown, the useful result is not always maximum coverage. The review should show where grafts give real visual value, where scalp micropigmentation may help contrast, and where donor limits make aggressive filling unwise.
The crown route below keeps medication response, SMP contrast, and graft spending as separate questions.

If the crown still has native hair, I want to see what treatment has done before spending grafts. If the crown is mostly bare and stable, then the conversation is about coverage, density expectations, and donor cost. The point is not to win an argument for medicine or surgery. It is to spend grafts where they will matter most.

Read this review excerpt
Every single one of my questions was answered and they made sure I had all the details I needed to make an informed decision.