
A Bad Cough Before FUE Can Change the Surgery Day Plan
Hearing yourself cough the night before FUE does not by itself mean the operation must be cancelled, but it is not something to hide. Tell the clinic early, even if travel is already arranged.
Send the facts that change the decision. Tell us when it started, whether it is improving or worsening, whether you have fever, wheeze, chest tightness, shortness of breath, and every cold or cough medicine you have taken. The plan may stay the same, be adjusted, or need medical review before travel or surgery day. Silence makes that decision less safe, because the clinic loses the chance to adjust travel, medicine, or timing early. Also say whether the cough comes in occasional clears or repeated fits when you lie flat.
Do not wait until arrival to test whether the cough is still important. A short video of repeated coughing, your temperature, and the medicines already taken can help the clinic decide whether travel still makes sense.
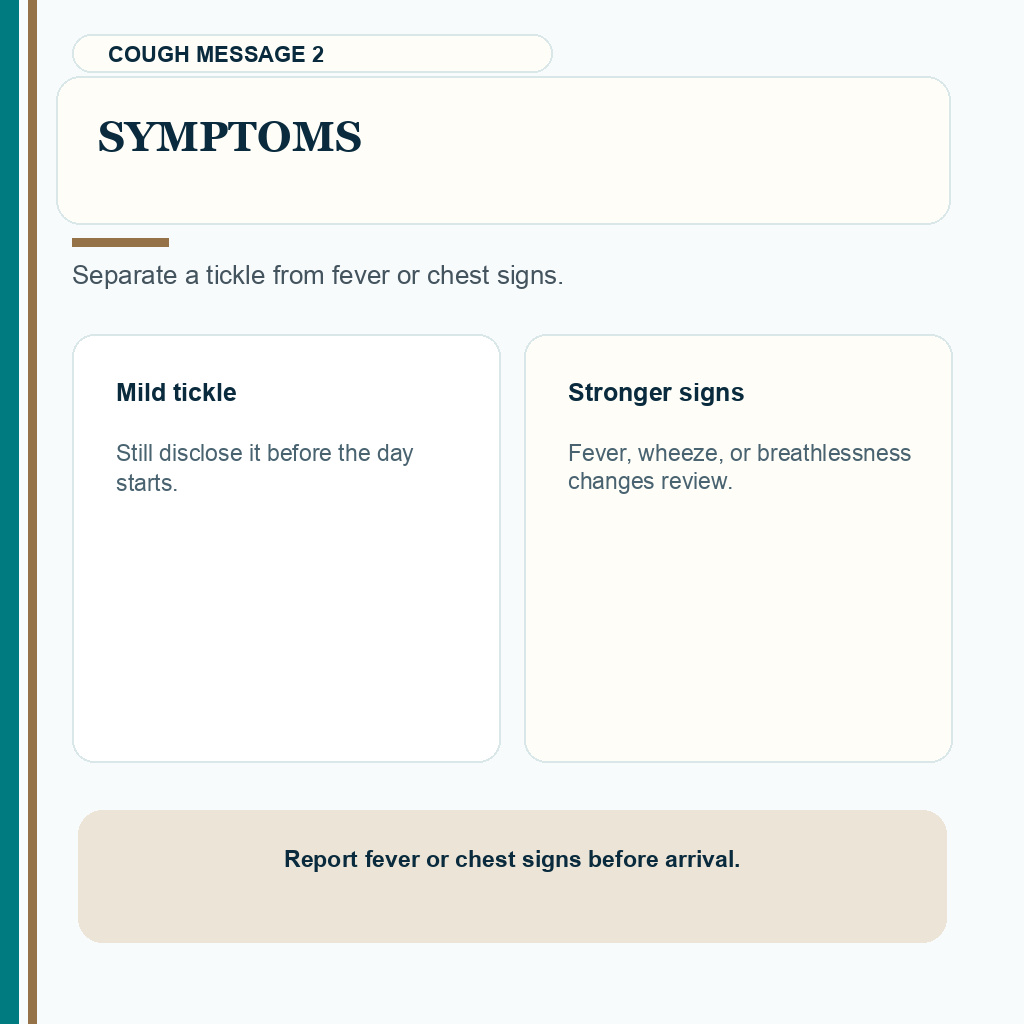
If the cough is active before FUE, send a precise update early. A mild leftover throat tickle is different from repeated coughing that shakes your body, keeps you from lying still, suggests an infectious illness, or requires several medicines taken together that could affect blood pressure, heart rhythm, sedation planning, or surgical day comfort.
I know why patients hesitate to say it. Flights, hotels, work leave, and the fear of losing the date can make silence feel easier. It is safer to adjust the plan early than to discover a cough that moves the body after the surgical day has started. A cough can be simple. It can also be the first sign that we need to slow down, ask better questions, or delay a decision until the medical picture is clearer.
Travel pressure should not decide this. A cough update sent before the flight gives the clinic more options than a cough discovered when the patient is already tired, anxious, and checked in for surgery.
A cough matters when it changes stillness, breathing, or infection control
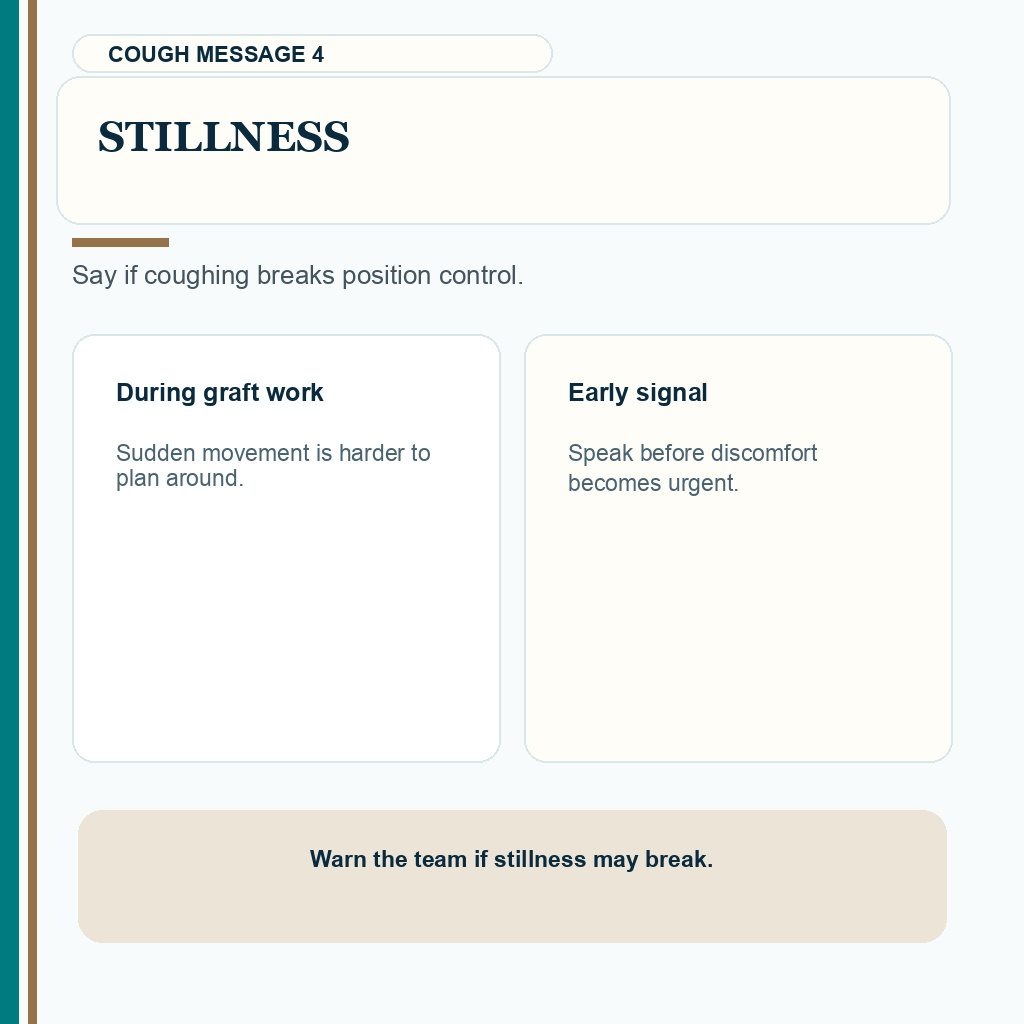
FUE is usually done while the patient is awake, still, and positioned for long periods. Coughing is not only a throat symptom in that setting. It can move the head or shoulders at the wrong moment, make prone or partly reclined positioning uncomfortable, interrupt local anesthesia steps, and make graft handling less predictable if repeated pauses are needed.
That does not mean every cough cancels hair transplant surgery. It means the cough has to be classified. A short dry tickle that is clearly improving is different from fever, phlegmy chest symptoms, uncontrolled asthma, a new wheeze, or a cough that comes in sudden bursts. I separate this from the broader cold or flu before hair transplant question because the decision here is narrower. I am checking whether the cough changes surgery day positioning, medicines, stillness, or infection control.
The other reason to disclose it is infection control and staff exposure. A patient may feel determined to continue, but the clinic must also think about other patients, the surgical team, and whether the symptom pattern suggests an active contagious respiratory illness. That judgment cannot be made safely from a hidden cough.
Also mention a recent positive flu test or positive COVID test, a known close exposure, new loss of smell or taste, and whether anyone travelling with you is sick. A negative test can help the discussion, but it should not be used to hide symptoms that are still active.
Send the cough update before travel becomes difficult to change
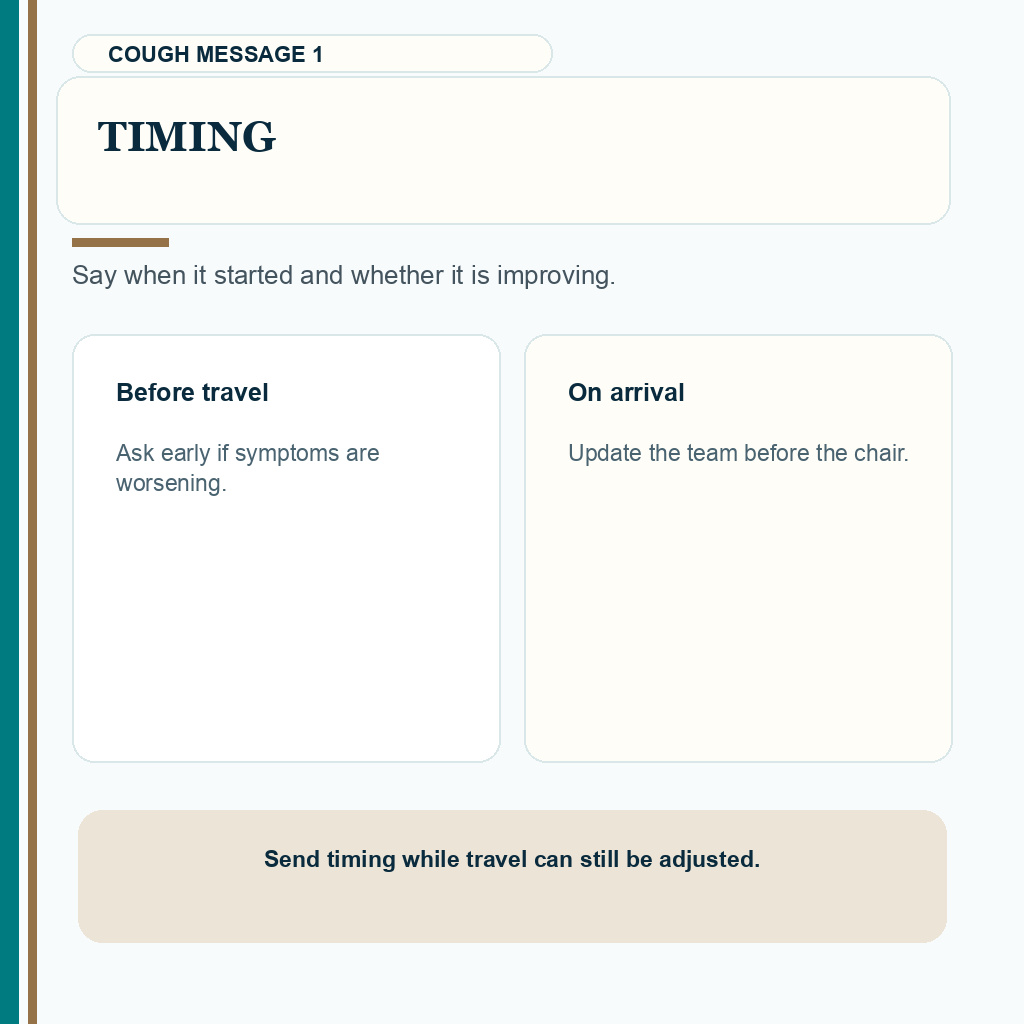
The best time to report a cough is before the travel plan becomes difficult to change. A message sent two or three days before flying gives the clinic more room to ask about fever, sleep, chest symptoms, breathing history, asthma history, and medication use. A message sent while you are already at the clinic gives fewer options.
If you have fever, a strong repeated cough, wheeze, chest tightness, shortness of breath, a positive COVID or flu test, or symptoms that are getting worse, do not board the flight silently and hope the surgery day will sort it out. Send the update before you travel, because the decision may be to delay the trip or arrange medical review before you come.
If you are already in Istanbul, the instruction is the same but the timing is tighter. Send the update as soon as symptoms change, even if you feel embarrassed or worried about losing the date. The clinic can still check temperature, breathing comfort, medicine use, position tolerance, and whether the day should proceed, but there are fewer clean options than before travel.
Send the facts plainly. Start with the day the cough began, whether it is dry or phlegmy, whether it is improving or getting worse, and whether it wakes you at night. Then add fever, sore throat, runny nose, chest tightness, wheeze, shortness of breath, asthma or inhaler changes, and the exact medicines you took. If you are taking decongestants, cough suppressants, antihistamines, pain relievers, antibiotics, or herbal products, list them instead of guessing what is relevant.
A useful message can be very simple. Write when it started, whether it is dry or phlegmy, whether you have fever, whether it becomes worse when you lie down, and the exact medicine and last dose. A clear message gives me more than a long explanation that hides the practical details.
If symptoms start on the morning of surgery, message or call before leaving for the clinic if you can, and bring every medicine box or bottle with you. The worst timing is to mention several medicines only after the preoperative conversation has already started.
This is also where travel timing matters. If you are asking about decongestants before FUE or a cold medicine that affects sleep, heart rate, or blood pressure, the clinic needs the name and dose. That review may be straightforward, but the team cannot review an unnamed tablet after the fact.

Cough medicines can change the medical review
A common mistake is to take several medicines to suppress the cough and then present the day as normal. That can create a second problem. Some cold and cough medicines can affect sleep, heart rate, blood pressure, dryness, anxiety, or alertness. Some patients also combine them with coffee, nicotine, supplements, painkillers, or prescribed medicines without realizing the surgical team needs to know.
Send a photo of the box or bottle, or write the active ingredients and last dose, not only the brand name. Combined cold remedies can include a decongestant, antihistamine, pain reliever, cough suppressant, caffeine, or codeine. Do not add extra painkillers, decongestants, supplements, nicotine, or caffeine just to push through surgery morning unless the medical team has reviewed them.
A cough medicine can make symptoms feel quieter for a few hours, but it does not prove the illness is safe for surgery. I still look at fever, chest symptoms, breathing comfort, sleep, contagiousness, and whether the medicine is hiding a problem rather than solving it.
I am not telling you to stop or start medicine without reviewing your own list. I am saying the clinic should know what you have taken before the plan is fixed. A medicine list is part of the same safety conversation as medication review before hair transplant.
If antibiotics are part of the story, the reason matters more than the tablet name. A prescribed course for a diagnosed problem that is improving is different from leftover tablets taken to protect the date. Send the diagnosis, antibiotic name, dose, start date, prescribing doctor, symptoms still present, and any diarrhea, rash, or dehydration. That belongs in the same timing review as antibiotics before hair transplant.
This matters even more if you have high blood pressure, palpitations, asthma, panic symptoms, or a history of chest problems. A cough medicine that seems ordinary at home can become important when combined with local anesthesia planning, adrenaline in the local anesthetic plan, long procedure time, and surgical stress.
If you already have high blood pressure, I want to know whether the medicine raised your readings or changed how you feel. If you notice racing heart, stimulant effects, or pulse changes, describe that the same way you would in a palpitations before hair transplant review. Hair transplant anesthesia and adrenaline can also become more relevant when cough medicine, caffeine, anxiety, or poor sleep changes your body’s response during the day.
This matters even when general anesthesia is not planned. FUE still means local anesthesia, long positioning, and long periods of stillness. Local anesthesia reduces some general anesthesia airway concerns, but it does not make fever, wheeze, shortness of breath, chest tightness, codeine cough syrup, sedatives, or stacked cold medicines irrelevant. If a sedative or anxiety medicine is being discussed, the team should know both the breathing symptoms and the cough or cold medicines first.
Repeated coughing can affect stillness and breathing comfort
During FUE, stillness is not about being strict with the patient. It protects surgical precision. A sudden cough can lift the shoulders, turn the neck, tighten the scalp, or interrupt a moment when the team needs stable access. One cough is usually manageable. Repeated bursts are different.
This becomes more important in a long session. If the cough appears whenever you lie down, talk, breathe through the mouth, or become anxious, we need to know before graft work is underway. When the cough also brings urgent restroom breaks or frequent position changes, say that before graft work starts. A planned pause is easier to manage than sitting up suddenly after the team has begun. The team may adjust position, pause at safer moments, change the order of steps, review whether the day should continue, or decide that postponement is safer than forcing a bad setup.
Graft handling also has its own timing rhythm. FUE graft outside the body time is one reason I want repeated coughing planned around, not discovered after extraction has started.
Chest symptoms and fever need a different level of review
A simple throat tickle is not the same as lower chest symptoms. Wheeze, chest tightness, shortness of breath, fever, marked fatigue, or a cough that is rapidly worsening deserve a more careful medical review before the patient travels or continues on surgery day. Patients with asthma should mention any change in inhaler use, recent attacks, night symptoms, or breathing limits.
Some symptoms should not wait for a hair transplant message. If you are struggling to breathe, have chest pain or pressure, cough up blood, feel suddenly confused, look pale or blue around the lips, or your fever or cough improves and then returns worse, treat that as a medical problem first. Seek urgent medical care and tell the clinic after you are safe.
A phlegmy cough with chest pain when coughing, blood in mucus, feeling too unwell for normal activity, or breathlessness is not the same as an upper throat tickle. Mucus color alone does not decide the case, but chest symptoms plus fever, worsening breathlessness, or feeling very unwell should move the discussion toward medical review before any elective procedure.
Sharing symptoms early is the useful step here. The purpose is to avoid a long elective procedure on a day when breathing comfort, infection status, or medication safety is uncertain. If asthma is part of the picture, asthma and hair transplant planning becomes part of the decision. If further checks are needed in selected situations, ECG and chest imaging before FUE may be part of that review.
Fever, wheeze, chest tightness, or shortness of breath should be reported before the day is confirmed.
Fever is also important because it suggests the body may be fighting an active illness. A patient may still feel determined, but elective surgery should not be treated like a test of willpower. When the facts point toward active infection or unstable breathing, the safer conversation may be rescheduling rather than squeezing the operation into the original date.
Use the cough timing board before the plan is fixed
The word “cough” is too broad by itself. Use the board to describe the pattern behind it before you send the clinic a message.
Cough before FUE decision splitter
Choose the closest pattern. The right response changes when cough timing, chest symptoms, medicine use, and stillness are different.
Mild improving tickle
A leftover dry tickle with no fever, no chest symptoms, and clear improvement may only need disclosure and monitoring. Send timing, current severity, and medicines anyway.
What may change on surgery day?
Early disclosure does not always make the plan dramatic. The clinic may simply document the cough, ask for another update in the morning, delay travel until symptoms are clearer, or decide after examination and medical review.
On the day itself, possible adjustments include a longer preoperative conversation, temperature or symptom check, position testing, different break timing, reviewing medicines, or delaying the start while the team decides whether it is reasonable to continue. If the cough is repeated, linked with chest symptoms, or combined with fever, the discussion may move toward postponement because the surgery is elective.
Consent also matters. You should understand the plan, the possible need to pause, and the point at which the team would not continue. That should be understood as part of hair transplant consent before surgery, not discovered after you are already on the chair.
Separate preoperative cough from coughing after the transplant
Patients often search for coughing because they worry about grafts popping out after surgery. That is a different question. After implantation, the main issue is protecting grafts from rubbing, pressure, trauma, and repeated checking. After surgery, I judge that concern through the separate sneezing and coughing after a hair transplant question.
Before surgery, the cough is a planning signal. It asks whether the body is well enough, whether the cough can be controlled safely, whether the patient can lie still, whether medicines need review, and whether the clinic should expose staff and other patients to a potentially contagious illness. The same symptom sits in a different decision frame before grafts are placed.
Please do not try to settle this question through online reassurance alone. A comment that one person coughed and was fine does not tell us whether your cough is dry, infectious, wheezy, related to medicine, interrupts sleep, or causes movement.
Four details matter more than a vague cough warning
A clear message saves time because it gives the clinic the four facts that change the decision. Tell us when the cough started, whether it is improving or worsening, what symptoms came with it, and what medicines, supplements, inhalers, nicotine, or caffeine you used.
Those details help separate a minor improving symptom from one that changes travel, admission, anesthesia discussion, positioning, or extraction timing.